
Antimicrobial resistance is a growing threat, and over-prescription of antibiotics is a major contributor to the global rise in bacterial resistance.
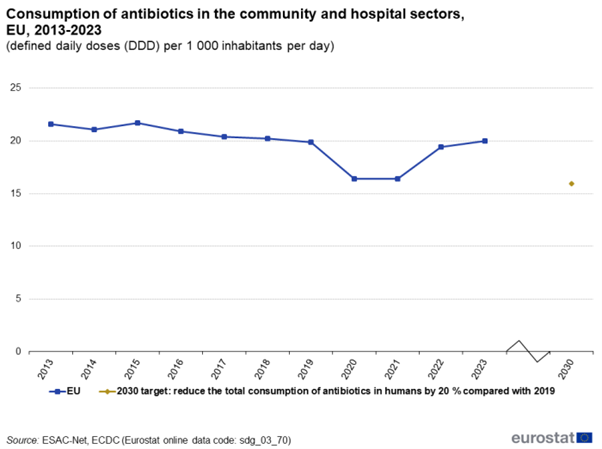
According to Eurostat, the overall trend in consumption of antibiotics has gone down in the EU, but further efforts are needed.
A study conducted by the Value-Dx project investigated whether point-of-care (POC) testing could reduce antibiotic prescription. The strategy included blood tests for inflammatory markers (CRP), throat swabs for Group A Streptococcus, and nasal swabs for influenza in patients for whom the doctor was considering antibiotics.
“POC testing is seen as an important tool in antimicrobial stewardship and its potential to reduce unnecessary antibiotic prescribing,” says Alike van der Velden of UMC Utrecht, the coordinating investigator of the PRUDENCE trial.
“POC tests have been shown to be effective in clinical trials, but when implemented into national guidelines and primary care, their effects have been limited. Evaluating POC tests in routine care was needed to get better insights into their effectiveness, potentially their cost-effectiveness and the barriers to implementing these tests in routine care.”
Participants in the trial were all randomly assigned to either receive usual care (without POC testing) or usual care with POC testing.
Before examining the patients and referring only to a form with their information, clinicians had to outline their likelihood of prescribing antibiotics.
Then, they examined the patients, carried out POC testing (if the patient was in the POC testing group) and made their final decision regarding treatment.
The results showed that the availability of these tests did not lead to a reduction in prescriptions, but the study unearthed important insights. It was clear from the results that integrating POC tests effectively into the usual primary care routine required more than just providing the tests.
“Overall we saw no difference between people who followed a complex POC testing strategy and those that were assigned to care without that strategy. That average effect hides a multiplicity of subtleties,” says Christopher Butler of Oxford University, one of the lead scientists who conducted the study.
“We did some analysis and found that when the clinician identified a high probability that they were going to prescribe antibiotics, they prescribed fewer antibiotics when using the POC testing strategy. But where their commitment to prescribing antibiotics was not as firm, they prescribed more antibiotics when using the testing strategy. The overall finding is that we need to find a better way to position these POC tests.”
Marta Wanat, a behavioural researcher working on the ValueDx project who led the data analysis of the PRUDENCE trial, said, “we have to think about POC tests as a behaviour-change intervention. We found that just giving people access to POC tests is not sufficient to reduce antibiotic prescribing.”
The impact of both clinician and patient perspectives
The Value-Dx PRUDENCE trial highlighted how important both clinician and patient perspectives were in antibiotic prescriptions. For instance, in some countries antibiotic use was more prevalent and expected by patients, especially parents of sick children. In those cases, clinicians felt pressure to prescribe antibiotics, even when test results suggested they were unnecessary.
Patients and clinicians were aligned on severity – when symptoms were severe, both clinicians and patients were more likely to choose antibiotics regardless of the test results.
Patients generally saw value in point-of-care testing, but their reactions varied.
Some felt reassured by the results, especially when tests confirmed the need for antibiotics or helped explain their condition. Others appreciated negative results, which supported their preference to avoid antibiotics due to concerns about side effects or antibiotic resistance.
The point-of-care testing also helped to convince patients who were sure that they needed antibiotics that they didn’t, when the tests were negative. This helped to demonstrate to patients that antibiotics are not always the appropriate treatment.
Trust in technology
When clinicians were unsure about whether to prescribe antibiotics or not, the tests seemed to help them to make a decision. But, when there was no doubt, the clinicians tended to trust their own judgment and experience over the test results.
Doubts over test performance in accurately predicting benefits from antibiotic treatment, and in precisely predicting whether non-antibiotic treatment strategies would be safe for patients, were a factor in this – if results conflicted with the clinicians’ own judgment, then questions were raised as to whether it was safe for patients to follow the treatment indicated by the test result. Evidence that it is safe for test results to over-ride clinical judgment is lacking, and clinicians’ repeated experiences of unanticipated results eroded trust.
Timing was another important factor. Tests may not detect infections accurately if used too early or too late in the illness, and this led clinicians to rely more on their own assessment.
Reducing antibiotic prescription rates is a complex game
A clear finding from the study was that accessibility to technology was not enough to reduce antibiotic prescribing.
“We have to think about this as a package of complex interventions rather than a simple straightforward solution,” Marta Wanat said. She outlined how the study had outlined different scenarios where POC tests could bring about behavioural change, as well as those where change is less likely.
“We can’t test everybody with a syndrome, and nor should we. The trial highlighted that particular care should be devoted to figuring out the place of testing in care pathways for maximum patient benefit,” says Butler. “There is no such thing as a negative trial – PRUDENCE takes the field forward in important ways. Attention should be focussed on identifying subgroups where tests will be beneficial and testing should involve more comprehensive behaviour changes and an implementation strategy, keeping the voices of the main actors – the patients and clinicians – at the centre.”
van der Velden pointed out how patient recovery was the same – about four days – in both the control and the group that received POC testing.
“If the trial had shown faster patient recovery in the POC testing group, it would have shown better targeting to patients benefiting from treatment. If the patient recovery time was slower in the POC testing group, it would have meant that antibiotics were inappropriately withheld from patients needing an antibiotic. We found similar recovery times in both groups, meaning that the changes made did not positively or negatively affect patient recovery.”
The study suggests that measures to support the effective implementation of POC tests to reduce antibiotic prescribing could include training clinicians in communication skills to better manage patient expectations, delaying decision-making until test results are in, improving education on how to interpret test results and educating patients to help them understand what the test measures and what the results mean.
By combining testing with these approaches, healthcare systems may be better able to reduce unnecessary antibiotic use – an important step in guiding the commissioning, placement and implementation of POCT testing in the community, and tackling antibiotic resistance.
VALUE-DX is supported by the Innovative Medicines Initiative, a partnership between the European Union and the European pharmaceutical industry.